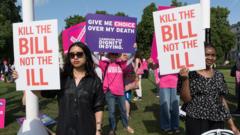
Kim Leadbeater, the Labour MP for Spen Valley, has reintroduced assisted dying legislation to Parliament, mirroring a bill that failed in the previous parliamentary session. Her move signals renewed momentum for one of Britain's most contentious medical ethics debates, with supporters arguing the time for reform has arrived.
The new bill follows the collapse of earlier assisted dying efforts. Leadbeater's decision to resubmit identical language reflects strategic persistence within pro-reform circles. She frames the reintroduction as finishing unfinished business, positioning assisted dying as inevitable rather than fringe policy.
Assisted dying remains deeply polarizing across Westminster and the broader electorate. Opponents cite concerns about vulnerable people feeling pressured to end their lives, religious objections, and the sanctity of the doctor-patient relationship. Advocates counter that terminally ill patients deserve autonomy over their deaths and that robust safeguards can protect against abuse. Countries including Canada, the Netherlands, Belgium, and Switzerland operate legal frameworks permitting medical assistance in dying, though each model varies considerably in eligibility criteria and oversight mechanisms.
Leadbeater's persistence reflects shifting public opinion on the issue. Multiple polls suggest majorities of British voters support legalizing assisted dying under strict conditions, though support fluctuates based on how questions frame the scenario. A YouGov survey from 2023 found 68 percent backing legal changes, though support drops when respondents consider specific edge cases or coercion risks.
The Labour government under Keir Starmer has navigated assisted dying cautiously. While individual MPs retain freedom to introduce Private Members' Bills, the government has not committed formal legislative time or whip direction, allowing backbenchers to pursue reform without triggering party-wide splits. This approach permits exploration of the issue without consuming ministerial bandwidth or forcing cabinet-level positions.
Previous attempts encountered procedural hurdles and sustained opposition from disability rights advocates, medical ethicists, and religious leaders. The Care Quality Commission and medical professional bodies including the British Medical Association remain divided on implementation. Disability campaigners argue that pressure to choose death reflects societal failure to provide adequate social care, housing support, and disability access rather than genuine free choice.
If Leadbeater's bill advances beyond initial readings, it will require negotiating substantive amendments addressing safeguards, eligibility criteria, and oversight protocols. Questions about whether the scheme covers mental illness, how to verify genuine consent, and what role psychiatric assessment plays remain contested. Any workable legislation would demand compromise between advocates seeking broad access and skeptics demanding narrow criteria protecting vulnerable populations.
Parliamentary time constraints remain the practical barrier. Private Members' Bills compete fiercely for limited slots, and assisted dying competes with hundreds of other backbench priorities. Success requires sustained lobbying, cross-party support, and parliamentary scheduling luck. Leadbeater's reintroduction demonstrates commitment but faces formidable procedural and political obstacles before reaching government consideration.